Who pays for a verified dispense, how drugs are screened, and the markets beyond the pharmacy bottle.
01
Drug screening
01.1
Drug Group Framework: Segment, Qualify, Prioritise
A Repeatable Screen, Not a Fixed List: 24 Drugs to 28
Three stages — what a missed dose costs, four mechanical gates, then whether it is worth tooling.
Stock photo
1
Stage 1 · Segment
By what a missed dose costs, and who therefore pays: A therapy loss (pharma first), B acute event (pharma on patent, plan once generic), C aggregate cost (plan-funded).
2
Stage 2 · Qualify — four gates, all must pass
Form: a tablet, or a non-gelatin capsule. Container: the patient receives the maker's bottle, not a blister wallet. Geometry: one opening size and one shape as the patient titrates and across suppliers. Regimen: chronic or cyclic with a defined plan — not PRN, not split tablets.
3
Stage 3 · Prioritise
A qualified drug is not automatically worth tooling: avoided cost per patient-year, patients on the molecule, who funds and for how long, moulds × sizes, and who signs.
U.S. patient counts: ClinCalc DrugStats (MEPS 2023) where listed, else Coledy sizing. Packaging: FDA NDC Directory. Shape and size: DailyMed. Running the gates is what removed four widely-prescribed specialty drugs from an earlier version of the tables that follow.
01.2
A Dose Is Not Always One Tablet
All 28 regimens read off FDA labelling — and the three things it changed.
Tablets per dose × doses a day, across the 28 therapies
1 tablet × once a day17 · 61%
1 tablet × twice a day5 · 18%
4 tablets × once a day3 · 11%
2 tablets × twice a day2 · 7%
Mixed strengths × once1 · 4%
Simultaneous — served
Several strengths at once, each bottle stable: one device per strength, each sensed and scored on its own, both in one app. Envarsus XR 0.75 / 1 / 4 mg · Lynparza 150 + 100 mg.
Sequential — out
One bottle whose tablet changes shape as the patient titrates. No number of devices fixes it. Jakafi round → oval → capsule · Cabometyx round → triangle → oval.
What the audit did not change twenty-one once-daily and seven twice-daily, confirmed against all 28 labels — the split already published, so no figure moved. What it did change the geometry gate now routes a split dose to a device per bottle instead of rejecting it, and pPDC caps per bottle.
What has not been measured: a four-tablet dose is four separate tilt-and-release actions. Field use so far has been on one-tablet regimens, so whether patience holds across four tilts is untested on five of the highest-value rows.
Regimen is tablets per dose × doses per day, read off FDA labelling for all 28 rows; shares round to 101%. Loading and ramp-up doses are named separately — Brilinta and Plavix load at two and four tablets, Eliquis opens DVT/PE at two, Venclexta ramps on a wallet.
01.3
The Screen Rejects More Than It Accepts
Every gate is run against FDA labelling — here is what failed, and the line that failed it. A list of drugs is a claim; a list of what failed and why is a method.
Out on geometry — the patient crosses shapes
Jakafi: starts at 10 mg twice daily and titrates in 5 mg steps — three shapes in normal use
Cabometyx: 60 → 40 → 20 mg reduction is routine, and 40 mg is a triangle
Xarelto: the DVT / PE course switches 15 mg to 20 mg and starts on a blister
Out on packaging — no bottle to sit on
Trikafta: co-packaged blister wallet
Ibrance: monthly box of weekly blisters
Imbruvica: folded blister cards
Verzenio: stored in the original blister
Out on shell — gelatin goes tacky
Revlimid · Gilenya · Tecfidera · Hydrea — the exclusion is the shell, not the shape
Kept, with the limit named
Venclexta: maintenance only — the four-week ramp-up is a wallet
Tagrisso: 80 mg oval, but 40 mg round on dose reduction
Keppra: all strengths are scored, so a half tablet is available
Four of five permanent exclusions fail on form or regimen, not geometry. Geometry decides among generics — and there it is usually recoverable, because what fails is that suppliers disagree on shape. The same lines that reject a molecule are the spec a partner can design to.
02
Target drugs
02.1
28 Priority Therapies, Three Groups
Six therapeutic areas, three entry groups — nine, eleven and eight drugs, screened from U.S. prescription data.
Drugs by therapeutic area
Oncology8
Cardiovascular7
CNS & psychiatry6
Infectious disease3
Immunology & transplant2
Metabolic & diabetes2
Group
What a failure costs
U.S. patients
Areas
A · Therapy loss
What a failure costsA therapy forfeited to resistance
U.S. patients~0.83M
AreasOncology · HIV · PAH
B · Acute event
What a failure costsRelapse and crisis
U.S. patients~3.2M
AreasCNS · oncology · transplant
C · Aggregate cost
What a failure costsSmall per patient, enormous in total
U.S. patients~51.4M
AreasCardiovascular · metabolic
A · Therapy loss — the manufacturer holds it
Oncology, HIV, pulmonary arterial hypertension. A missed dose costs the therapy itself. The payer buys these drugs at $48,000–$200,000 a patient-year, but a day never dispensed is a day never sold — so the maker carries the loss.
B · Acute event — the payer, twice
CNS and psychiatry, transplant, cardiology. A missed dose becomes an event — a relapse, a rejection, an admission. The payer buys the drug and then the admission that follows.
C · Aggregate cost — the payer, and it is scored
Statins, RAS antagonists, oral diabetes agents. No single missed dose matters; the accumulation does. Cheap generics, yet the payer still loses — all three triple-weighted Medicare adherence measures sit here.
Two funding routes, never zero: a manufacturer whose therapy is lost when a dose is missed, or a payer already scored on the measure. A drug with neither is not on this list — that is what the screen tests for, and why the list is 28 and not 2,800.
Counted per drug — a patient treated for three of these appears three times, and carries three devices. Source: ClinCalc, CDC, FDA.
02.2
Group A — Therapy Loss
High-cost therapies where a missed dose lets resistance or progression in. ~0.83M U.S. patients.
Stock photo
Who: about 0.83M U.S. patients on high-cost branded therapy — HIV, cancer and pulmonary arterial hypertension.
A missed dose lets resistance or progression in, and the therapy itself can be lost.
At stake: drug costs of about $45,000–$200,000 per patient a year (table below).
Who pays first: the drug's maker — the therapy and its label are its own.
Drug
Indication
U.S. patients
Drug cost / yr
What a missed dose does
Biktarvy
IndicationHIV-1
U.S. patients430K
Drug cost / yr$48,000
What a missed dose doesResistance mutations emerge
Dovato
IndicationHIV-1
U.S. patients180K
Drug cost / yr$45,000
What a missed dose doesTwo drugs, less margin for error
Xtandi
IndicationProstate cancer
U.S. patients55K
Drug cost / yr$200,000
What a missed dose doesAndrogen blockade lapses
Nubeqa
IndicationProstate cancer
U.S. patients25K
Drug cost / yr$130,000
What a missed dose doesAndrogen blockade lapses
Erleada
IndicationProstate cancer
U.S. patients30K
Drug cost / yr$140,000
What a missed dose doesAndrogen blockade lapses
Lynparza
IndicationOvarian & breast cancer
U.S. patients35K
Drug cost / yr$180,000
What a missed dose doesMaintenance window closes
Venclexta
IndicationCLL & AML
U.S. patients30K
Drug cost / yr$160,000
What a missed dose doesRemission depth erodes
Tagrisso
IndicationNon-small-cell lung cancer
U.S. patients30K
Drug cost / yr$165,000
What a missed dose doesEGFR resistance emerges
Opsumit
IndicationPulmonary arterial hypertension
U.S. patients12K
Drug cost / yr$175,000
What a missed dose doesClinical worsening, then escalation
Why Xtandi is the only branded addition
The 40 mg film-coated tablet is round and holds one shape across 160, 120 and 80 mg — every reduction the label allows. The 40 mg soft-gel capsule ships in the same bottle size and fails on its shell, so the tablet product has to be specified. It also brings a new drug maker; more HIV rows would add patients, not companies.
Checked and out: CDK4/6
One ships in weekly blisters; the other instructs storage in the original blister. Neither reaches the patient in a bottle.
Patients: ClinCalc, CDC, FDA. U.S. basis — generics at CMS NADAC plus dispensing fees, branded at list price. Avoided cost per failure event, from the sources on the next table.
02.3
Group B — Acute Event
A missed dose ends in relapse, admission or a costlier therapy. Mostly generic — paid for by the plan. ~3.2M U.S. patients.
Stock photo
Who: about 3.2M U.S. patients — mental health, epilepsy, cancer, transplant and autoimmune conditions.
A missed dose ends in relapse, a seizure, rejection or hospital admission — or a switch to a costlier therapy.
At stake: about $12,000–$95,000 per failure event avoided (table below).
Who pays: the maker while the drug is on patent, the health plan once it is generic — most of this list is generic.
Drug
Indication
U.S. patients
Drug cost / yr
Avoided cost
What a missed dose does
Aripiprazole (generic)
IndicationMDD, adjunctive
U.S. patients1.26M
Drug cost / yr$1,270
Avoided cost$30K
What a missed dose doesRelapse, then admission
Keppra
IndicationEpilepsy
U.S. patients400K
Drug cost / yr$2,000
Avoided cost$12K
What a missed dose doesBreakthrough seizure
Olanzapine (generic)
IndicationSchizophrenia, bipolar
U.S. patients379K
Drug cost / yr$1,518
Avoided cost$30K
What a missed dose doesRelapse, then admission
Rexulti
IndicationMDD, adjunctive
U.S. patients300K
Drug cost / yr$16,000
Avoided cost$30K
What a missed dose doesRelapse, then admission
Xeljanz
IndicationRheumatoid arthritis
U.S. patients300K
Drug cost / yr$60,000
Avoided cost$70K
What a missed dose doesFlare, then a biologic switch
Latuda (generic)
IndicationBipolar depression
U.S. patients250K
Drug cost / yr$300
Avoided cost$30K
What a missed dose doesRelapse, then a switch to an injectable
Vemlidy
IndicationChronic hepatitis B
U.S. patients120K
Drug cost / yr$27,500
Avoided cost$80K
What a missed dose doesViral rebound, liver injury
Aubagio (generic)
IndicationMultiple sclerosis
U.S. patients60K
Drug cost / yr$850
Avoided cost$21K
What a missed dose doesRelapse and accrued disability
Gleevec (generic)
IndicationCML
U.S. patients50K
Drug cost / yr$700
Avoided cost$60K
What a missed dose doesMolecular response lost
Abiraterone (generic)
IndicationProstate cancer
U.S. patients45K
Drug cost / yr$2,400
Avoided cost$70K
What a missed dose doesProgression, then next line
Envarsus XR
IndicationTransplant immunosuppression
U.S. patients35K
Drug cost / yr$30,000
Avoided cost$95K
What a missed dose doesRejection, then graft loss
Why three generics, and why they sit here
Every molecule that cleanly passes the four gates turns out to be generic — a branded oncology product is packaged for unit-dose control, a long-marketed generic for a pharmacy to count into a vial. Generic means no brand owner paying, and that means plan-funded — which is what Group B is.
Patients: ClinCalc, CDC, FDA. U.S. basis — generics at CMS NADAC plus dispensing fees, branded at list price. Avoided cost per failure event, from the sources on the next table.
02.4
Group C — Small per Patient, Enormous in Total
Cheap, widely used tablets where adherence drives Medicare Star Ratings. ~51M U.S. patients. ★ = Star Ratings measure drug.
Stock photo
Who: about 51M U.S. patients on cheap, widely used tablets for heart and metabolic conditions.
A missed dose works slowly: LDL rebounds, stroke risk returns, blood sugar drifts toward complications.
At stake: small per patient, enormous in total — about $12,000–$33,000 per failure event avoided (table below).
Who pays: the health plan — adherence on these drugs feeds Medicare Star Ratings.
Drug
Indication
U.S. patients
Drug cost / yr
Avoided cost
What a missed dose does
★ Lipitor
IndicationDyslipidemia
U.S. patients29.4M
Drug cost / yr$140
Avoided cost$33K
What a missed dose doesLDL rebounds, plaque progresses
★ Crestor
IndicationDyslipidemia
U.S. patients11.8M
Drug cost / yr$150
Avoided cost$33K
What a missed dose doesLDL rebounds, plaque progresses
Eliquis
IndicationAtrial fibrillation
U.S. patients3.5M
Drug cost / yr$6,500
Avoided cost$33K
What a missed dose doesStroke risk returns
Plavix
IndicationAfter a coronary stent
U.S. patients1.8M
Drug cost / yr$140
Avoided cost$18K
What a missed dose doesStent thrombosis
★ Entresto
IndicationChronic heart failure
U.S. patients1.5M
Drug cost / yr$7,300
Avoided cost$12K
What a missed dose doesHeart failure decompensates
★ Rybelsus
IndicationType 2 diabetes
U.S. patients1.5M
Drug cost / yr$12,000
Avoided cost$15K
What a missed dose doesGlycaemic drift to complications
★ Januvia
IndicationType 2 diabetes
U.S. patients1.4M
Drug cost / yr$4,500
Avoided cost$15K
What a missed dose doesGlycaemic drift to complications
Brilinta
IndicationAcute coronary syndrome
U.S. patients0.5M
Drug cost / yr$5,000
Avoided cost$18K
What a missed dose doesPlatelets reactivate on a twice-daily gap
★ marks drugs that count toward Medicare Star Ratings adherence measures — the reason a payer pays for a low-cost generic.
Patients: ClinCalc, CDC, FDA. U.S. basis — generics at CMS NADAC plus dispensing fees, branded at list price. Avoided cost per failure event, from the sources on the next table.
02.5
Where Each Avoided-Cost Figure Comes From
Avoided cost is what one failure event costs when a dose is missed. Each figure is a published health-economics result — not a Coledy estimate.
Failure event
Drugs
Avoided cost
Published source
Ischemic stroke, first year
DrugsEliquis · Lipitor · Crestor · Plavix
Avoided cost$33K
Published sourceMedicare non-valvular AF cohort — incremental first-year cost $32,900
Graft loss, back to dialysis
DrugsEnvarsus XR
Avoided cost$95K
Published sourceUSRDS 2021 — Medicare dialysis payment $87,000–$99,000 per patient-year
Relapse, then admission
DrugsRexulti · Latuda · aripiprazole · olanzapine
Avoided cost$30K
Published sourceRelapse admissions reported at $20–40K; schizophrenia ~$14,000 a year excess Medicaid cost
Myocardial infarction
DrugsPlavix · Brilinta
Avoided cost$18K
Published sourceInside CKD pragmatic review (2022 USD) — mean $18,294 per event
Heart-failure admission
DrugsEntresto
Avoided cost$12K
Published sourceJ Manag Care Spec Pharm 2022;28:157 — mean $11,552
Diabetic complication
DrugsJanuvia · Rybelsus
Avoided cost$15K
Published sourceJ Med Econ 2014 (2012 USD) — event-year cost $9,041 to $71,714
Relapse in multiple sclerosis
DrugsAubagio
Avoided cost$21K
Published sourceJ Manag Care Spec Pharm 2023 review — a relapsing year costs $4,390–21,345 more
Advanced liver disease
DrugsVemlidy
Avoided cost$80K
Published sourceJ Hepatol 2019;70:24 — decompensated cirrhosis $142,870 a year vs $18,619
Breakthrough seizure
DrugsKeppra
Avoided cost$12K
Published sourceEpilepsy Behav 2015;51:40 — $14,491 vs $3,215 in matched controls, six months
Step-up to a costlier therapy
DrugsXeljanz
Avoided cost$70K
Published sourceAnnual cost of the injectable biologic the patient moves onto
Drug cost on an acquisition basis: CMS NADAC per unit × 365 plus twelve dispensing fees for generics; list price for branded rows. Aubagio uses median generic WAC.
03
Therapy areas
03.1
Real-Time Evidence to Stop Controlled Drug Diversion
Stock photo
Legacy tracking stops at the pharmacy counter. Coledy verifies the dose after it — at the dose level.
14.4Mpeople misuse controlled drugs in the U.S. each year
8.9Mopioid misuse — 62% of the total
80,000+opioid overdose deaths a year
Step
Legacy tracking
With a verified dispense record
1 · Prescription
Legacy trackingCovered (EMR)
With a verified dispense recordCovered
2 · Pickup
Legacy trackingCovered (claims)
With a verified dispense recordCovered
3 · Dose event
Legacy trackingBlind spot
With a verified dispense recordVerified in real time
EMR · Rx issued
Claims · pickup
Auth · patient phone
Verify · GPS location
Evidence · single-tablet log
Outcome · anomaly alert
Coledy layer: GPS verification + single-tablet log turn the untraceable dose event into settlement-grade evidence.
Regulatory A top-priority issue for the DEA; FDA imposes REMS obligations on pharma — a clear, mandated payer.
Traction: early interest from government / regulators at U.S. expos (pre-pilot, not yet executed). Source: CDC WONDER & SAMHSA (2024–2025 basis).
03.2
Obesity Therapy: Capturing the Oral GLP-1 Market
Two approved pills in fifteen months and a phase 3 field behind them. Every one of them is a tablet in a bottle.
Roche, Novo amycretin and others — oral programmes in trials
Tablet, not capsule
Compressed tablets carry the dose and the absorption enhancer in a smaller pill.
Daily, at home, for years
No clinic visit records the dose. Persistence is the whole variable.
Qualified by form, not brand
An oral obesity drug is screened the same way as any other.
The moisture cap is a part, not a barrier. Oral semaglutide keeps its drying agent in the cap. On a round bottle the Coledy build is an add-on closed by a single child-resistant closure — certified to 16 CFR Part 1700 as a separate article under its own test programme, the tested configuration being the closure assembled with the device on the bottle — so the desiccant and the seal have to sit within that closure. Not yet demonstrated: equivalent moisture performance.
Approvals: FDA. Phase status as most recently reported by each company. Not in the financial model — this widens an existing route, it does not add a forecast line.
04
Data & AI
04.1
Healthcare AI: Ground-Truth Adherence Data
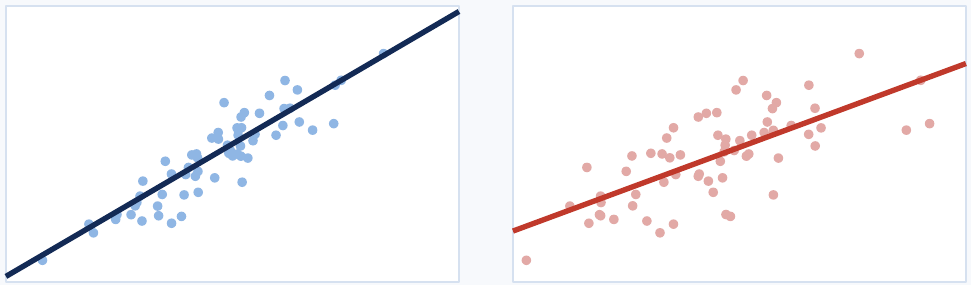
A predictor measured with error drags its own coefficient toward zero — and adherence is measured with error everywhere.
The same relationship, measured without error (left) and with error (right). Simulated at λ = 0.60, fixed seed — the fitted slope falls to 0.61.
Reliability λ
0.9
0.8
0.7
0.6
0.5
True effect ÷ published
0.91.11×
0.81.25×
0.71.43×
0.61.67×
0.52.00×
β_obs = λ · β_true, λ = σ²ₓ / (σ²ₓ + σ²ᵤ) < 1 always. Sensitivity, not a point estimate — no published λ exists for claims-based PDC.
Statistics room
Cite attenuation — the effect is understated.
Data-science room
Cite label noise — a lower ceiling and a bigger data bill.
Either room
The fix is a better label, not a better model.
A verified dispense raises λ on the adherence variable toward 1. That does not make a model smarter — it removes the attenuation that was hiding the effect. This holds for non-differential error; the systematic over-reporting in self-report shifts the mean and needs separate treatment.
Spearman, Am J Psychol 1904 (correction for attenuation); Carroll, Ruppert, Stefanski & Crainiceanu, Measurement Error in Nonlinear Models, 2nd ed., 2006; Frénay & Verleysen, IEEE Trans Neural Netw Learn Syst 25(5), 2014.
04.2
Healthcare AI Trains on Inferred Adherence, Not Verified
Stock photo
A fill, an opening and a memory are all inferences — a verified dose never reaches the model.
Labelled dose observations — one patient, one year, once daily
Pharmacy claims — one record per fill12
Patient self-report12
Cap sensor — an opening, not a tablet365 · 0 verified tablets
Coledy STPV — a tablet leaving the bottle365 verified
Claims record a purchase, cap sensors record an opening, apps record a memory. The valve records a tablet leaving the bottle, at a timestamp.
Classical attenuation: a predictor measured with error biases its own coefficient toward zero. Every published adherence–outcome estimate is therefore a floor, not a ceiling.
Value Every adherence model in the field trains on an estimate of the variable it is trying to predict. Coledy produces the measured value — for Coledy's models and for a partner’s.
It cannot be bought or backfilled
04.3
Predictive Value from Adherence Data
Precision dispense data fused with partners' lifelog signals is designed to train models that predict risk and generate real-world evidence.
1
Data fusion
Fuse verified pPDC with partners' lifelog data — fill the clinical-data gap with high-resolution behaviour.
2
Model development
Learn individual patterns to flag adherence drop-off risk; use adherence–biomarker correlations to predict complications.
3
AI on adherence
Analysis on measured adherence strengthens clinical development and regulatory readiness.
Not in the forecast — no data-licensing contract exists.
04.4
Digital Health Networks: Daily Social Network Engagement
Stock photo
Platforms Bring Reach; Coledy Brings a Verified Dispense Record
A scheduled, device-triggered event every day — engagement the platform does not have to manufacture.
A daily reason to open the app
A care circle worth subscribing for
Health content it can stand behind
Consent first Anything shared beyond the patient — a carer, a circle, a feed — is opt-in per recipient and revocable. Adherence is health data, not a status post.
Illustrative partner-app mock — the 95% and the battery level are not measured.
04.5
Supplements Claim Efficacy With No Proof of Dosing
Four categories sold on a dosing regimen — and none can show the regimen was followed.
Blood pressure
Daily · same time
Consistent dosing maximises the reduction; irregular dosing raises cardiovascular risk.
Glucose
Twice daily · with meals
Strict pre- or post-meal timing; irregular dosing causes spikes and control failure.
Weight management
Daily · steady level
A steady blood level is required; missed doses cut the effect.
NAD+ / longevity
Daily · no gaps
Long-term use maintains levels; stopping erases the gains.
Regimens are the manufacturers' own label directions. A verified record that the regimen was dispensed is the missing half.
05
Channels
05.1
The Channel That Needs No Market Entry
An interventional trial supplies its own bottles — so the dispensing format of the country the patient lives in does not apply.
$180Bof the $300B+ a year is direct trial cash waste — Phase II/III programmes abandoned to statistical noise and adherence failure
Non-adherence inflates σ, not the effect
A subject who misses doses does not weaken the drug — they widen the variance around it. The trial then needs more subjects, or reports a false negative.
The expensive failure is finding out late
A non-adherent subject identified in week two can be replaced. The same subject identified at database lock has consumed a full arm of cost and cannot be replaced at all.
The container gate is a retail constraint
Around 85% of oral solids dispensed in Europe are blistered, and press-through packs are standard in Japan. A drug maker running a trial ships investigational supply in whatever container the protocol specifies.
The buyer is clinical development
A different budget, decision-maker and contract from the commercial channel. One signature at headquarters covers every site in the study.
Korean and Japanese drug makers are a near market
In a retail argument Korea is small. Here the contract is signed at a headquarters within reach, and the sites can be anywhere.
R&D waste figures: Tufts CSDD and Watanabe (2018). A post-authorisation study on a marketed drug is different — the patient collects an ordinary pack, so that half needs the valve-less Universal build and a bottle market. No clinical contract has been signed.
05.2
Connected-Care Infrastructure for B2B & B2G
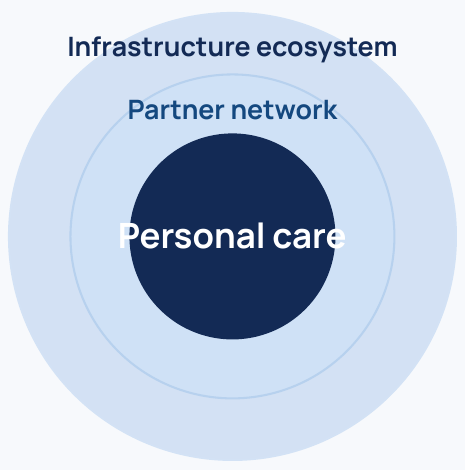
The dose-data layer scales — from the individual to community care to smart cities.
Government (B2G)
Chronic-disease management reimbursement
Municipal (B2G)
Senior-living safety-care programmes
Payers
Value-based health-data payments
Providers
Adherence-monitoring protocols
Pharma
Clinical and RWE data services
Construction (B2B)
Healthcare wall-pad systems
Data flow: individual › community › urban infrastructure › policy. Multi-sector B2B & B2G value creation across pharma R&D, clinical data, and global platform expansion.
Illustrative — no counterparty approached.
05.3
Seven B2B Channels, and How Each One Signs
The go-to-market plan targets seven B2B channels across pharmacies, hospitals, distributors and digital platforms.
Remote and online pharmacy
Local pharmacy network
Hospital partnerships
Global partnerships
Pharma distribution
Caregiver network
Digital channels
These are target channels for the go-to-market plan. None is contracted today — they are channels a licensee sells into; Coledy does not operate them.
Inquiries
For licensing, partnership or investment inquiries, please write to the address for your area.